
Science explained
SPG4 in children: what parents need to know
SPG4 can begin in childhood. What is known about onset, diagnosis, care today, inheritance and research, explained for parents, with medical sources.

We are a nonprofit from Romania dedicated to accelerating research into genetic therapies for SPG4 — an inherited neurological condition that can begin in childhood. We fund rigorous science, stand alongside families, and publicly report every amount we receive.
24-month goal: €3,000,000
Reporting begins with the first verified donation
How we verify amountsHereditary spastic paraplegia type 4 is a genetic neurological condition in which the long nerve fibres that carry movement signals from the brain to the legs gradually deteriorate. In some children, the first signs appear in the early years of life.
For a child, SPG4 usually means legs that become increasingly stiff (spastic) and weak, making walking harder over the years. It does not affect only children — for many people it begins in adulthood — and its course varies widely even within one family: a parent and their child can follow very different paths. That is why understanding the condition, and researching treatments that could change its course, matters to every family.

We are dedicated to accelerating research into genetic therapies for SPG4, with one clear goal: better lives for the children living with this condition and, when science allows, effective treatments available through medically appropriate pathways.
We support projects chosen for their scientific quality, with clear objectives and a documented budget, that can bring treatments for children with SPG4 closer.
We bring parents, clinicians and researchers to the same table, so research priorities reflect what truly matters to children.
Every verified donation appears in our public reporting. We clearly separate money received from pledges and from amounts committed to projects.

We aim to raise €3,000,000 over 24 months for research, scientific collaboration and medically appropriate access pathways — so that one day, children with SPG4 have real treatment options.
This is a fundraising ambition, not the price of an existing treatment. Every project we support will have a documented budget, published before it receives funds.
Received and verified
—
of the €3,000,000 goal
No verified amounts yet
We only show money received and confirmed by bank statement, the platform's official report or the payment processor. The first update will appear here as soon as it is verified.
Verified amounts only. Sponsorship pledges are not included.
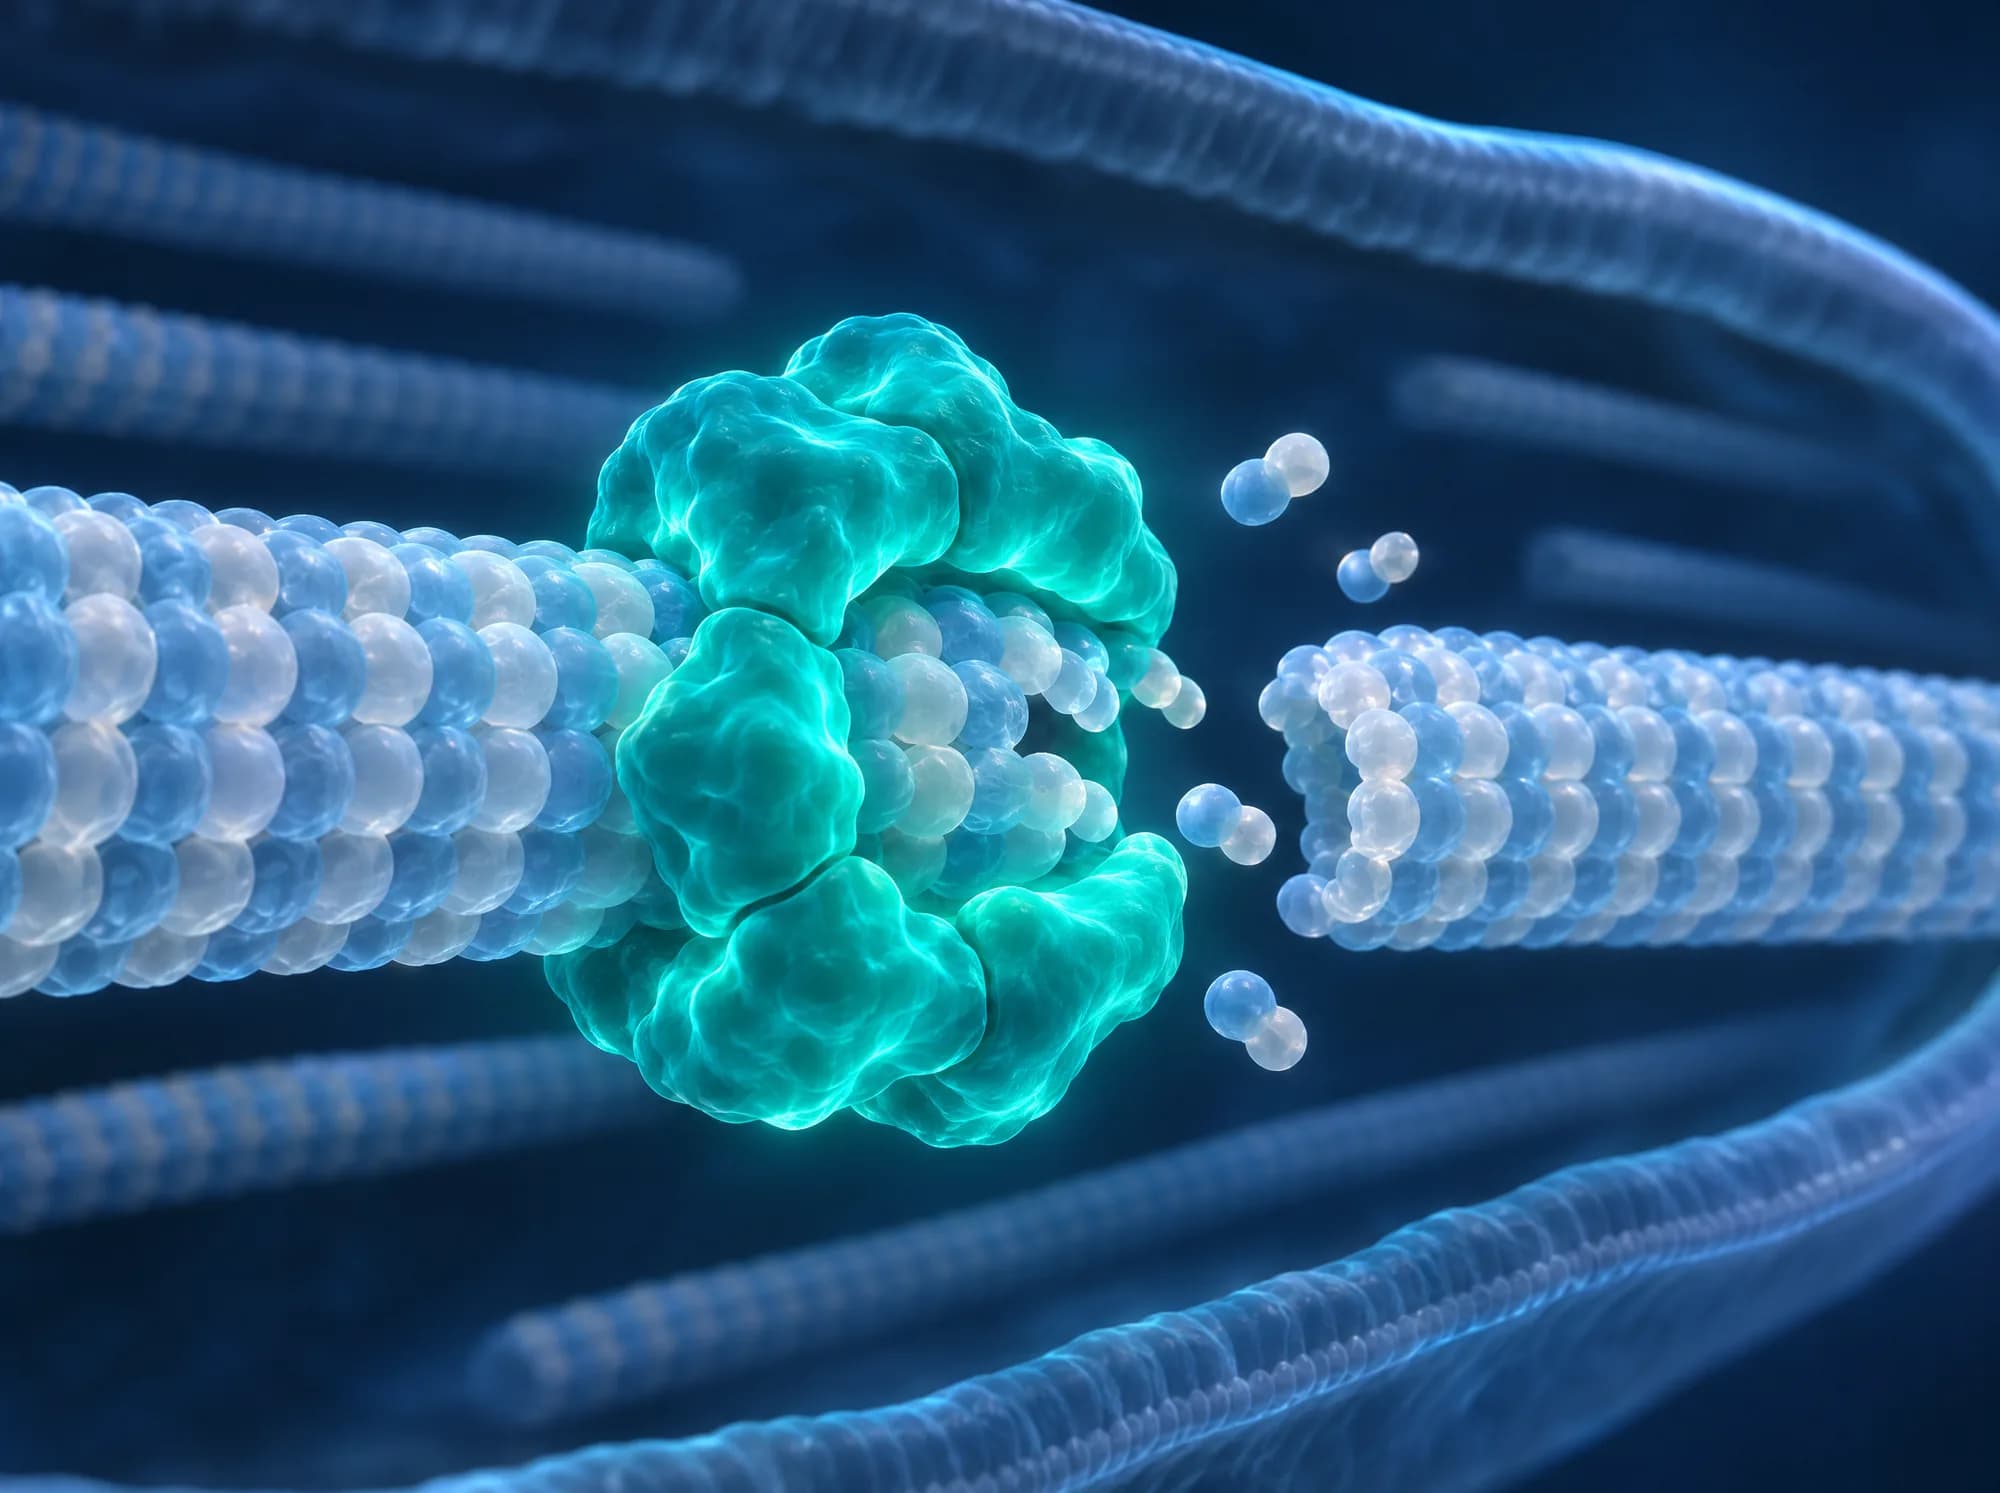
The SPAST gene holds the instructions for spastin, a protein that cuts microtubules — the filaments that form the internal skeleton of nerve cells and along which materials travel down the axon.
It sits on chromosome 2 (region 2p22.3). In people with SPG4 — children or adults — one of the two copies of the gene carries a pathogenic variant.
An enzyme in the AAA ATPase family. It assembles into six-part rings that sever microtubules, helping the cell reorganise its internal network of ‘tracks’.
The motor neurons that run from the brain down the spinal cord have some of the longest projections in the body. They depend on efficient internal transport, and the far ends of these axons are the first to be affected in hereditary spastic paraplegia.
Restoring spastin levels (for example by blocking its breakdown), ‘silence-and-replace’ gene therapy, inhibiting the enzyme HDAC6, or drugs acting on microtubules. In one study, gene therapy given to newborn mice prevented symptoms — which is why researchers also ask whether the timing of treatment matters. These results come from cells and animal models: no approach has yet been tested in children or adults with SPG4.
Rare diseases seldom attract enough commercial investment to get past the earliest stages of research. Organisations founded by families can fund exactly those stages and build the infrastructure future studies depend on.
Preclinical studies are often the hardest to fund. Their results can open the door to public grants and larger investments.
We help teams working on SPG4 and related conditions share data, models and expertise.
We represent children with SPG4 in Romania and their families in conversations with doctors, researchers and authorities.
Cell models, patient registries and data on how the condition evolves, including in children, make every future study faster and more robust.
Science explained
SPG4 can begin in childhood. What is known about onset, diagnosis, care today, inheritance and research, explained for parents, with medical sources.

Science explained
What an SPG4 diagnosis means, how it shows itself, how it is inherited, how it is confirmed and what can be done for symptoms today. In plain language, with medical sources.
Science explained
The Melpida gene therapy for SPG50 has given many families hope. We explain what it showed, why SPG4 is a different disease and what can realistically be learnt from it.

A sponsorship partnership can directly support a research project for children with SPG4, with dedicated reporting, responsible visibility and a contract that complies with Romanian sponsorship law.
See partnership optionsClear summaries of studies relevant to SPG4, campaign progress and financial reports. No spam; unsubscribe at any time.

Support research with a one-off or monthly donation, or join us as a volunteer, ambassador or partner.
AI-generated illustrative image. It does not depict real people, patients or partners.
Parodi L, Rydning SL, Tallaksen C, Durr A (2019). Spastic Paraplegia 4. GeneReviews®, University of Washington, Seattle (posted 2003; updated 13 June 2019).
PMID 20301339Last verified: 6 November 2026
The core clinical reference for SPG4: frequency, onset, symptoms, inheritance, diagnosis and symptomatic care.
Parodi L, Fenu S, Barbier M, et al. (2018). Spastic paraplegia due to SPAST mutations is modified by the underlying mutation and sex. Brain 141(12):3331–3342.
PMID 30476002Last verified: 6 November 2026
Study of 842 people with SPG4: onset, penetrance and variant types.
Hazan J, Fonknechten N, Mavel D, et al. (1999). Spastin, a new AAA protein, is altered in the most frequent form of autosomal dominant spastic paraplegia. Nature Genetics 23(3):296–303.
PMID 10610178Last verified: 6 November 2026
Discovery of the SPAST gene and the spastin protein.
Errico A, Ballabio A, Rugarli EI (2002). Spastin, the protein mutated in autosomal dominant hereditary spastic paraplegia, is involved in microtubule dynamics. Human Molecular Genetics 11(2):153–163.
PMID 11809724Last verified: 6 November 2026
First evidence that spastin regulates microtubule dynamics.
Evans KJ, Gomes ER, Reisenweber SM, et al. (2005). Linking axonal degeneration to microtubule remodeling by Spastin-mediated microtubule severing. Journal of Cell Biology 168(4):599–606.
PMID 15716377Last verified: 6 November 2026
Purified spastin is sufficient to sever microtubules.
Roll-Mecak A, Vale RD (2008). Structural basis of microtubule severing by the hereditary spastic paraplegia protein spastin. Nature 451(7176):363–367.
PMID 18202664Last verified: 6 November 2026
First structural model of the spastin hexamer.
Blackstone C (2012). Cellular pathways of hereditary spastic paraplegia. Annual Review of Neuroscience 35:25–47.
PMID 22540978Last verified: 6 November 2026
Defines hereditary spastic paraplegias as length-dependent distal axonopathies of the corticospinal tracts.
Solowska JM, Baas PW (2015). Hereditary spastic paraplegia SPG4: what is known and not known about the disease. Brain 138(Pt 9):2471–2484.
PMID 26094131Last verified: 6 November 2026
The M1 and M87 spastin isoforms and hypotheses about disease mechanism.
Piermarini E, Baas PW (2026). SPG4 hereditary spastic paraplegia: from etiology to therapy. Movement Disorders 41(10):2592–2605.
PMID 42538614Last verified: 6 November 2026
The most recent review of SPG4 causes and therapeutic directions.
Sardina F, Carsetti C, Giorgini L, et al. (2024). Cul-4 inhibition rescues spastin levels and reduces defects in hereditary spastic paraplegia models. Brain 147(10):3534–3546.
PMID 38551087Last verified: 6 November 2026
Flies and patient cells: restoring spastin levels reduces defects.
Piermarini E, Guha S, Qiang L, et al. (2026). Intracerebroventricular SPAST-AAV9 gene therapy prevents manifestation of symptoms in a mouse model of SPG4 hereditary spastic paraplegia. Molecular Therapy 34(3):1729–1742.
PMID 41311060Last verified: 6 November 2026
‘Silence-and-replace’ gene therapy in newborn mice: prevented symptoms. Not tested in humans.
Mohan N, Ramakrishnan S, Sun X, et al. (2026). Modeling spastic paraplegia 4 with corticospinal motor neuron-enriched cortical organoids reveals genotype-phenotype and HDAC6-targetable pathology. Cell Reports 45(3):117036.
PMID 41739645Last verified: 6 November 2026
Organoids and mice: HDAC6 inhibition rescues axonal degeneration.
Sandate CR, Szyk A, Zehr EA, et al. (2019). An allosteric network in spastin couples multiple activities required for microtubule severing. Nature Structural & Molecular Biology 26(8):671–678.
PMID 31285604Last verified: 6 November 2026
Cryo-EM structure of spastin with a glutamate peptide in its central pore.
Han H, Schubert HL, McCullough J, et al. (2020). Structure of spastin bound to a glutamate-rich peptide implies a hand-over-hand mechanism of substrate translocation. Journal of Biological Chemistry 295(2):435–443.
PMID 31767681Last verified: 6 November 2026
Human spastin structure and the hand-over-hand mechanism.